
 Comparing Mebendazole with Albendazole: Which Is Better?
How Mebendazole and Albendazole Work Differently
Clinicians often describe antiparasitic therapy as both art and science; these two drugs illustrate that tension. One focuses on gut-limited activity with poor systemic absorption, while the other reaches tissues and systemic parasites after metabolism.
Mechanistically, both disrupt microtubule formation but differ in pharmacokinetics and metabolites. Albendazole converts to an active sulfoxide enabling broader distribution; mebendazole remains largely unchanged, concentrating where intestinal worms live and reproduce.
Clinically this means choice depends on target tissue, infection load, and patient factors like age, pregnancy, and drug availability.
| Drug | Distribution |
|---|---|
| Albendazole | Systemic use |
| Mebendazole | Intestinal |
Which Parasites Respond Better to Each Drug
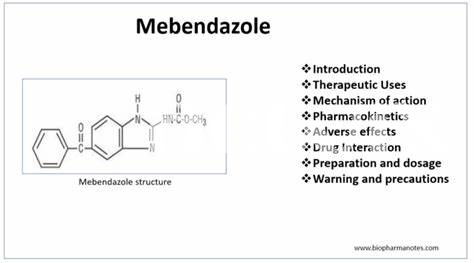
In crowded clinics and rural kitchens, simple symptoms hide worms, and choice of drug matters. Mebendazole shines for common intestinal infections—especially pinworm and many roundworms—because it concentrates in the gut and clears luminal parasites effectively.
Albendazole’s systemic absorption gives it broader reach, making it preferred for tissue-invasive helminths like neurocysticercosis and hydatid disease and other systemic infections. It treats intestinal nematodes too, especially when larvae migrate or cysts develop.
Hookworm and whipworm respond to either drug, but resistance patterns and disease severity guide choice. Strongyloides and systemic infections usually call for albendazole or ivermectin instead of mebendazole.
Ultimately parasite biology, infection site and patient factors determine drug choice; clinicians balance spectrum, safety and access overall.
Dosing Differences, Absorption and Practical Use
Clinicians balance convenience and biology when choosing therapy; one-pill regimens appeal, yet absorption nuances dictate effectiveness across intestinal and systemic infections.
Mebendazole often requires multiple doses or chewable forms for intestinal worms, aligning with its low systemic absorption but strong local activity.
Albendazole’s better systemic uptake after fatty meals makes it preferable for tissue-invasive parasites, though dosing schedules and monitoring differ.
Practical use hinges on parasite type, patient age, pregnancy status, and access; clear instructions and adherence optimize outcomes and limit resistance. Regular follow-up and reporting aid public health efforts.
Safety Profiles, Side Effects, and Pregnancy Considerations
When clinicians weigh choices, profiles matter: mebendazole often causes mild gastrointestinal upset or transient headache, while albendazole may have broader systemic effects like liver enzyme elevations. Monitoring labs can catch early problems.
Allergic reactions are uncommon but possible with either agent; more serious hematologic issues are rare. Risk rises with prolonged or high-dose therapy, especially in systemic infections requiring extended regimens.
Pregnancy alters the balance: albendazole is generally avoided in the first trimester and often during pregnancy unless benefits outweigh risks; mebendazole is also typically withheld early in gestation. Expert consultation is advised.
In practice, choosing the drug involves infection type, duration, patient comorbidities and monitoring capacity to minimize harm while maximizing cure, plus counseling.
Efficacy, Resistance Patterns and Clinical Outcomes
Clinicians often recall a child cured after a single dose, yet trials tell a richer tale: variable cure rates depend on species, burden and regimen. Head-to-head studies sketch patterns clinicians can apply practically today reliably.
Mebendazole shows strong activity against many intestinal worms when given appropriately, while albendazole’s broader tissue penetration improves efficacy for larval or migrating forms. Dose timing and single versus repeated courses shape outcomes significantly in practice.
Emerging reduced susceptibility appears sporadic and localized; surveillance data remain limited. Molecular markers are being explored, but routine resistance testing is uncommon. Pragmatic selection often balances reported failures, local epidemiology, and drug availability at clinics.
Patient outcomes hinge on correct diagnosis, appropriate dosing, and follow-up. Repeat treatment or alternative regimens improve cure where initial response is poor. Shared decision-making with patients increases adherence and optimizes long-term control and reduces relapse.
| Drug | Typical advantage |
|---|---|
| Mebendazole | Effective for many intestinal helminths |
Cost, Availability, Access and Choosing Wisely
Prices vary widely between brand and generic formulations, shaping treatment choices for individuals and programs in low resource settings seeking affordable safe care.
Supply chains, national procurement, and inclusion on essential medicine lists determine whether clinics can reliably stock either drug for mass campaigns locally.
Clinicians should balance price with diagnostic certainty, resistance data, and expected side effects when selecting therapy for an individual patient in practice.
Public health programs emphasize cost effectiveness and safety; informed prescribing, stewardship, and patient counseling maximize benefit while minimizing unnecessary use and shortages locally.